Case conferences for GPs managing ADHD
The psychiatrist, psychologist, OT, social worker and dietitian your ADHD patient needs, in one Medicare-funded video conference you convene. Free for GPs.





How a case conference supports your state’s ADHD pathway
Select your jurisdiction.
New South Wales
Complex cases should be co-managed with psychiatric or paediatric input. A psychiatrist or paediatrician must be involved above the dose ceilings.
The psychiatrist or paediatrician advises you on the patient and the dose by video, and the conference note records their involvement.
Pathway as published by NSW Health, Feb 2026. Confirm your scope with your own health department before prescribing; a conference is not a specialist review and does not satisfy a condition that calls for one.
Queensland
Complex cases should involve paediatricians, psychiatrists and psychologists.
All three advise you on one call, and the conference note records their advice.
Pathway as published by Qld Government, Nov 2025. Confirm your scope with your own health department before prescribing; a conference is not a specialist review and does not satisfy a condition that calls for one.
Western Australia
GPs outside the accredited program must have a shared-care arrangement with a specialist to continue treatment.
The conference is that shared care in practice: you and the specialist discuss the patient together, on record.
Pathway as published by WA Government, Aug 2026. Confirm your scope with your own health department before prescribing; a conference is not a specialist review and does not satisfy a condition that calls for one.
South Australia
GPs are expected to take a whole-person approach to assessment and prescribing.
A psychologist, OT and dietitian advise you in one conversation, so the plan covers more than medication.
Pathway as published by RACGP newsGP, Feb 2026. Confirm your scope with your own health department before prescribing; a conference is not a specialist review and does not satisfy a condition that calls for one.
Victoria
A permit generally requires specialist diagnosis and periodic specialist review.
Between reviews, the specialist advises you by video and the conference note documents it for the permit file. It does not replace the review.
Pathway as published by Vic Department of Health, Aug 2026. Confirm your scope with your own health department before prescribing; a conference is not a specialist review and does not satisfy a condition that calls for one.
Tasmania
Authority renewal must be supported by evidence of continued specialist review. Shared care with paediatricians and psychiatrists is recommended for children and complex cases.
The paediatrician or psychiatrist advises on the patient with you by video, and each conference note is a dated record of their involvement. It does not replace the review itself.
Pathway as published by RACGP newsGP, May 2026. Confirm your scope with your own health department before prescribing; a conference is not a specialist review and does not satisfy a condition that calls for one.
Australian Capital Territory
Non-routine cases must be individually approved.
Work the case through with a psychiatrist on a call, and attach the conference note to the application.
Pathway as published by ACT Government, Feb 2026. Confirm your scope with your own health department before prescribing; a conference is not a specialist review and does not satisfy a condition that calls for one.
Northern Territory
Each authorisation must be supported by a psychiatrist or paediatrician.
That specialist advises you by video, and each conference note records their support.
Pathway as published by RACGP, Jun 2026. Confirm your scope with your own health department before prescribing; a conference is not a specialist review and does not satisfy a condition that calls for one.
How a case conference supports patient outcomes
Across five trials, shared care improved functional outcomes for ADHD in every model studied.
Effect sizes 0.3–0.7
Case conferencing generally
- Patient problems properly identified
- More effective care plans,
- Better clinical decision-making,
- Fewer hospitalisations and ED presentations
- Better symptom management and quality of life,
- Lower overall healthcare costs
Who can join an ADHD case conference

Diagnosis, dose, review interval, co-occurring conditions.
CBT, psychoeducation, parent training, anxiety and low mood.
Executive function, routines, sensory needs, work and classroom.
Family, school, housing, work, NDIS; the carer.
Appetite and weight on stimulants, growth, sleep, eating.
Side effects, heart rate and blood pressure between reviews.
Structured activity for sleep, mood and regulation.
Interactions, formulations, adherence, medicines review.
What the child’s day actually looks like.
Minimum three participants, each providing a different kind of care. A parent or carer may attend without counting toward the minimum.
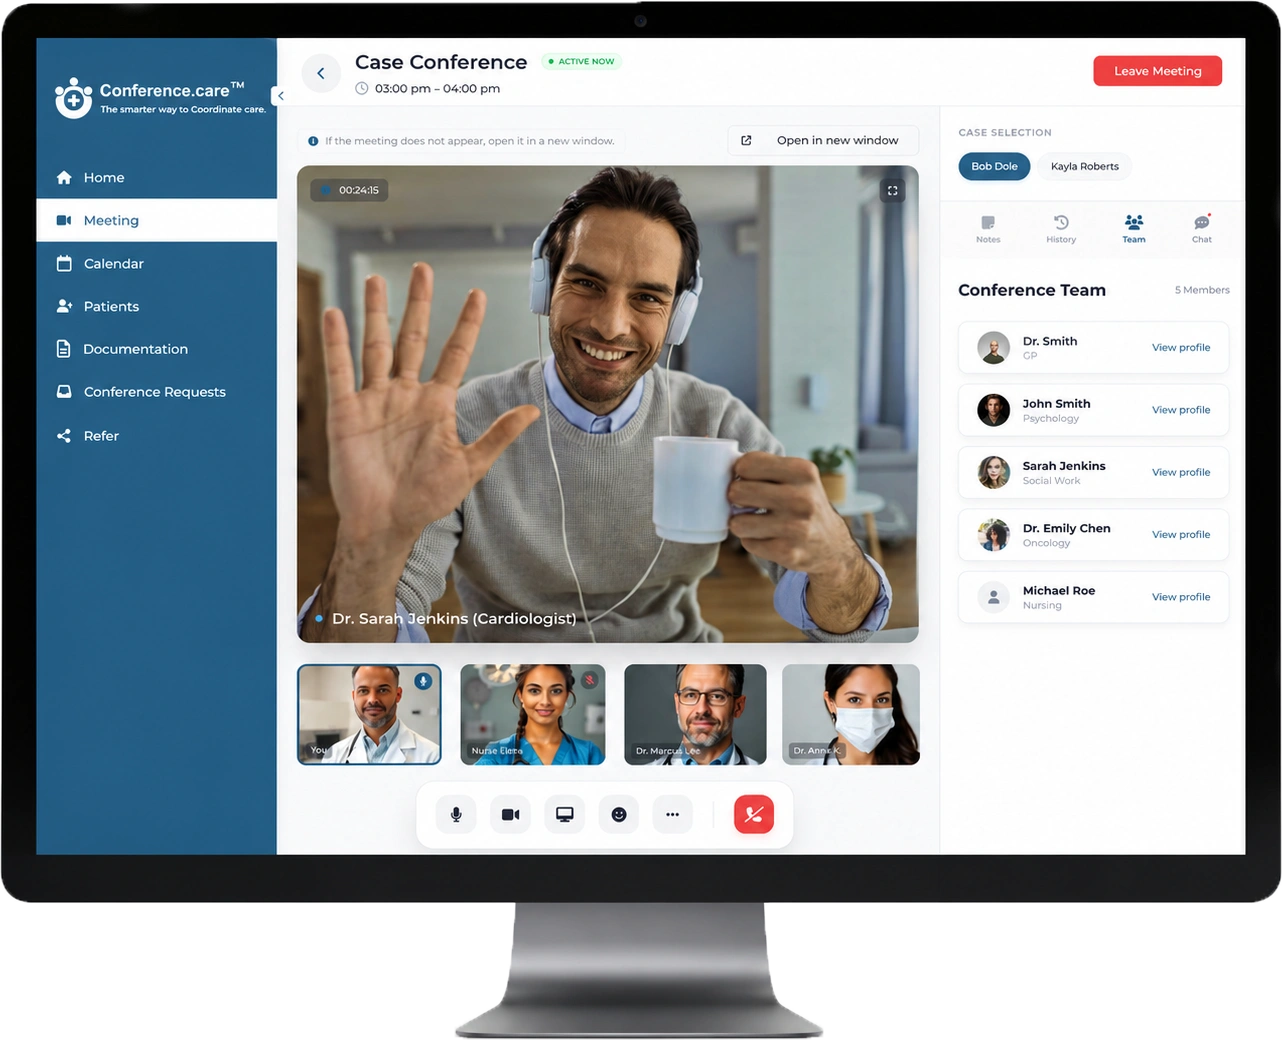
How a conference runs on Conference.care
Add the patient
Note the presenting problems and name anyone already treating them. Consent is captured by SMS.
A team is brought together
Existing providers are invited. A missing discipline is filled from anywhere in Australia. You sign off the team.
Talk it through
Secure video, no install, notes written during the call. You claim your item; each participant claims theirs. Refer afterwards in one click, if you choose.
The Medicare items
Conference duration, frequency and composition remain clinical decisions for the coordinating practitioner.
Common questions
Does an ADHD patient qualify?
Community items: yes. The schedule’s note says all Medicare-eligible patients are eligible; the test is the team, not the diagnosis.
Mental health items: for a patient referred for treatment under Better Access (a mental health treatment plan and referral) or on an eating disorder plan. ADHD is on the Better Access list, so a patient already seeing a psychologist under a plan usually qualifies.
Does it count as the specialist review my permit requires?
No. It is a discussion between clinicians, not a consultation with the patient. It funds the specialist conversation between reviews and leaves a dated record of it.
Does the patient attend?
They may, and must consent either way. On the mental health items they should be offered the option. A parent, carer or teacher who attends does not count toward the three-provider minimum.
My patient has a mental health treatment plan. Can I still conference them?
Yes, as long as the conference is separate from developing or reviewing the plan. Keep the two on different days; same-day claims have been rejected as ‘associated’.
How often?
GP community items carry no limit. Allied health participation items cannot be claimed within three months for the same patient unless their condition or circumstances change significantly. The mental health items are expected no more than about four times in twelve months. All limits are per patient.
What about the complex neurodevelopmental items, 82001–82003?
They are for patients under 25 with a complex neurodevelopmental condition, defined by impairment across two or more domains, or a listed disability. ADHD is not named. Use the two families above unless that assessment has been made.
What does it cost the practice?
Nothing. No subscription, no per-conference fee, no share of your rebate. Medicare funds each clinician through their own item. The pilot is one patient, no commitment.
Run a pilot conference for one ADHD patient
Free for GPs. You convene and claim the item; a team is brought together and rostered to suit your patient.
General information for clinicians, current at the dates shown. Not clinical, financial or legal advice, and not a substitute for your jurisdiction's prescribing rules, which are the only authority on scope. Item numbers and explanatory notes are as published in the Medicare Benefits Schedule; check the current schedule before claiming. Conference duration, frequency and composition remain clinical decisions for the coordinating practitioner.